Industry · Health · Emergency
Emergency departments: physician performance · crowding · result by site
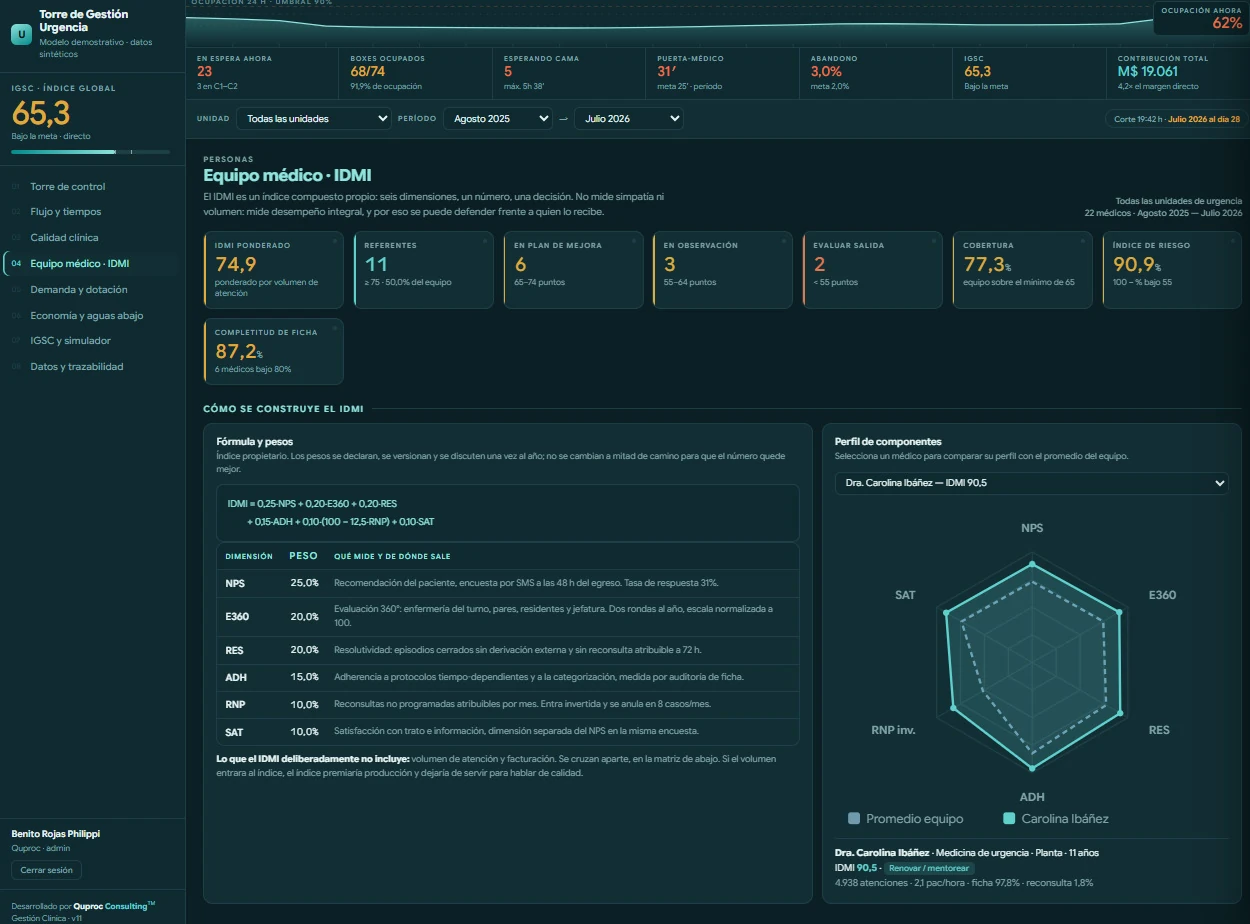
Performance score of the medical staff crossed with the financial result of each site, with an automatic decision per clinician.
What it measures
Physician performance · crowding · result by site.
The views it generates
Executive dashboard of the group by site and specialty.
Financial summary with normalized margin and risk distribution.
Medical staff ranking with an automatic decision by profile.
Consolidated view of the group compared across sites.
Digital record of the patient and the clinician in seconds.
Threshold alerts configurable by the organization.
Where the data comes from
What is already recorded is what comes in: the emergency department and triage system, the shift and coverage spreadsheet, output per clinician, billing by site and the treatment-time records. Nothing is migrated and no one's system is replaced.
The performance of the medical staff and the financial result of each site are read on the same axis and over the same period. Margin is normalized across sites so the comparison holds, instead of a table of apples and oranges.
Alerts that fire on their own
Thresholds configurable by site, specialty, shift and clinician. Sustained crowding at peak hours and clinicians below target flag themselves, with the training recommendation already attached.
- CRITICALOne site in sustained crowding above the threshold at peak hours.
- WARNINGClinicians below target: automatic training recommendation.
- INFOMargin by site normalized and comparable for the board.
One engine, every industry
What changes between modules is the unit the industry already decides with and the thresholds that trigger its alerts. The calculation layer, the traceability and the delivery are identical. How the model works, in four stages.
This module falls under the same plans as the rest. See plans and pricing.
Other industries modeled
Send us one month of shifts and visits and we will show you what comes out of it.
Thirty minutes is enough to see whether your emergency network fits the model as it already stands or whether it is worth adjusting to your sites and your medical staff. No cost, no commitment.